 Skip to main content
Dr Harsh Shah · Intestinal and Small Bowel Surgeon · Apollo Hospital, Bhat, Gandhinagar and Gota OPD, Ahmedabad
Intestinal tuberculosis is cured by tablets, not by an operation. A six-month course of antitubercular therapy — ATT — treats the disease itself; surgery is reserved for the complications it leaves behind, chiefly a blockage that will not settle, a perforation, or a narrowing that has turned to scar. Most patients never need theatre at all. The two decisions that matter are therefore made before any operation is discussed: is this tuberculosis, or is it Crohn’s disease or a cancer wearing the same appearance; and if the bowel does have to be opened, how little of it can be removed. Dr Harsh Shah sees this disease week in and week out at Apollo Hospital, Bhat, and the commonest reason it is missed is a request form, not a rare presentation.

Shah’s Gastro, Cancer & Robotic Surgery Centre
Dr Harsh Shah
MS, MCh (Surgical Gastroenterology), DrNB (Surgical Gastroenterology)
Registered with Gujarat Medical Council, Reg. No. G-38738
Intestinal and Small Bowel Surgeon
· Apollo Hospital, Bhat, Gandhinagar · Gota OPD, Ahmedabad
Trained at high-volume surgical gastroenterology programmes and qualified twice over in the speciality, Dr Harsh Shah operates on the small bowel as a dedicated part of his practice. Intestinal tuberculosis is the clearest example in abdominal surgery of a disease where the surgeon’s main job is to decide not to operate — to get tissue, get the diagnosis right, start the tablets, and keep the resection as small as possible if one becomes unavoidable. Google rating 4.89 from 216 reviews at the Gota clinic, and 4.94 from 17 reviews at the Apollo, Bhat listing.
Tuberculosis in the abdomen settles most often where the small bowel joins the large bowel — the ileocaecal region — and it can also line the peritoneum or sit in the mesenteric lymph nodes. It thickens the bowel wall, ulcerates it, and in time replaces the ulcer with scar that narrows the passage. That is why the commonest way it reaches a surgeon is not as an infection at all, but as recurrent, partial blockage: cramping pain after meals, distension, vomiting, weight loss, a low fever in the evenings.
The picture it makes is shared by three other conditions, and separating them is the whole clinical task. A thickened, inflamed ileocaecal segment in an adult can be tuberculosis, Crohn’s disease, or a cancer or lymphoma of the caecum and terminal ileum. It can also appear as a firm lump in the right lower abdomen that looks and feels exactly like an appendicular mass. There is no scan that settles this. Only tissue does.
What should make anyone suspect tuberculosis in particular: repeated episodes of partial obstruction that keep resolving with a drip and rest, night sweats, anorexia and loss of weight over months, ascites with a lymphocyte-rich fluid, anaemia with a high ESR and a low albumin, and a background of contact with tuberculosis, previous tuberculosis, diabetes, malnutrition, chronic kidney disease or any cause of reduced immunity.
Two facts about testing are worth carrying into the consultation because they mislead so many families. A normal chest X-ray does not exclude abdominal tuberculosis — most patients with intestinal tuberculosis have no active disease in the lungs at all. And the Mantoux skin test and the IGRA blood test are supportive at best: in this country a large share of healthy adults test positive simply from past exposure, so a positive result tells you a person has met the organism, not that this bowel disease is due to it.
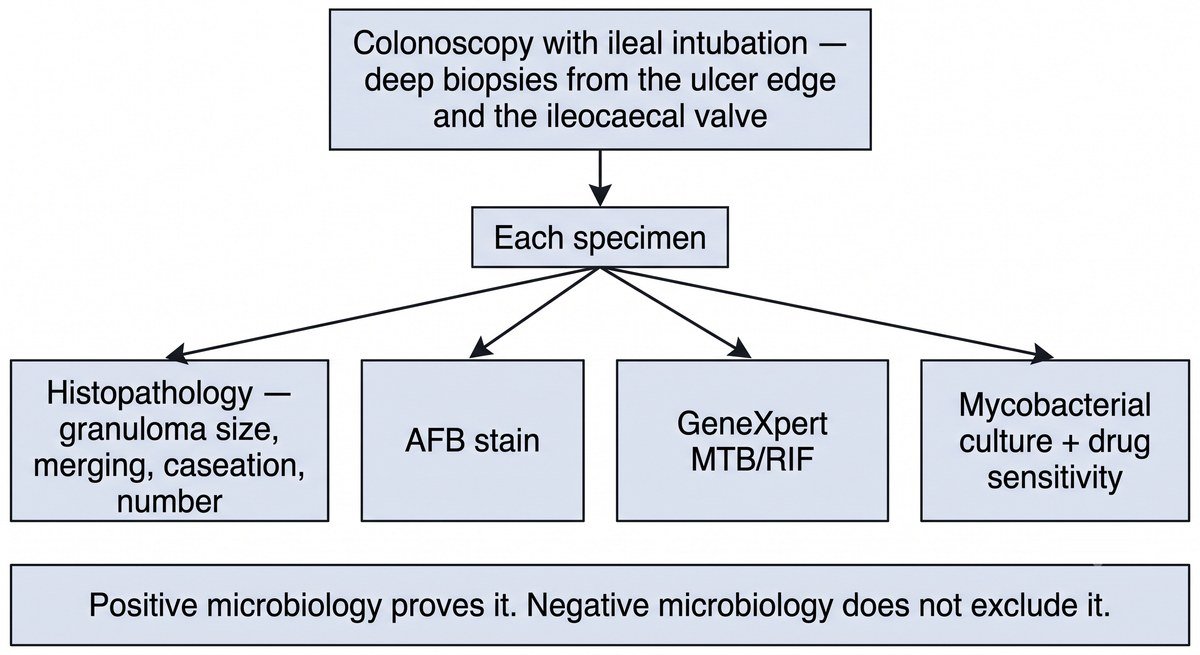
The diagnosis is made on tissue, and it is made on how that tissue is handled. A colonoscopy is performed with the scope passed into the last part of the small bowel — ileal intubation — and multiple deep biopsies are taken from the edges of the ulcers and from the ileocaecal valve. Each specimen must then be sent for four things, not one: histopathology, an AFB stain, GeneXpert (a molecular test for the tuberculosis bacterium and for rifampicin resistance), and mycobacterial culture with drug-sensitivity testing. Sending the biopsy for histopathology alone is the commonest single reason this diagnosis is missed in practice.
Two technical points decide whether the biopsy is informative. The granulomas that mark tuberculosis sit below the surface lining, so a shallow pinch of mucosa can miss them entirely — the biopsies have to be deep and there have to be several of them, taken from the ulcer edge rather than its floor. And the pathologist should be asked explicitly about the character of the granulomas: are they large, merging into one another, with the central breakdown called caseation, and are there many of them per section? “Granulomas present” on a report does not answer the question. The joint Indian working-group recommendations from the pathologists’, gastroenterologists’ and colitis-foundation bodies set out exactly what the report should say, and Dr Harsh Shah’s requests are written to that standard.
Alongside the tissue:
One rule runs underneath all of it: malignancy is excluded in parallel, never afterwards. A mass at the ileocaecal junction in an adult is treated as tuberculosis, Crohn’s disease or cancer until the tissue says which. And a negative AFB smear or a negative GeneXpert does not clear tuberculosis — the yield of these tests from bowel specimens is genuinely low. A positive result proves the diagnosis; a negative one proves nothing.
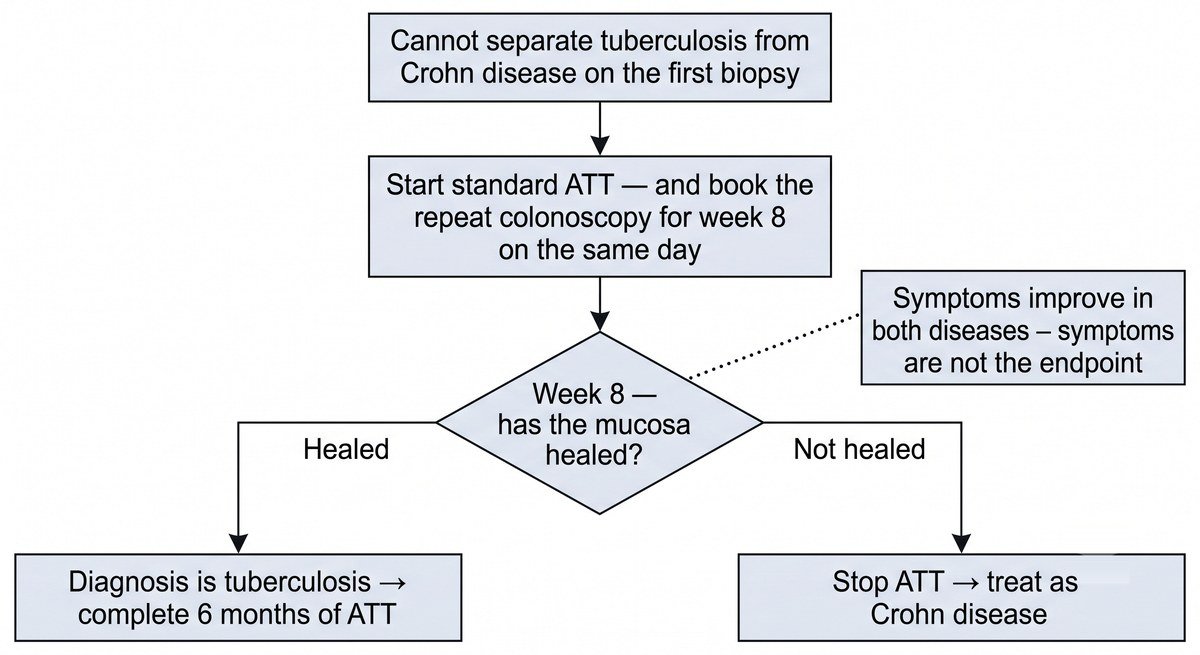
In a substantial minority of patients the two cannot be separated at the first visit, however good the endoscopy and however careful the pathologist. That is a recognised situation, not a failure, and it has a defined way out: a structured trial of antitubercular treatment with a repeat colonoscopy booked for eight weeks at the moment the tablets are started. What is looked for at eight weeks is healing of the lining — not whether the patient feels better.
Features that point one way or the other, as they are actually weighed in clinic:
| Feature | Points towards intestinal tuberculosis | Points towards Crohn’s disease |
|---|---|---|
| Fever and night sweats | Usually present | Usually absent |
| Blood in the stool | Uncommon | Common |
| Long-standing diarrhoea | Less prominent | Prominent |
| Disease around the anus — fistula, fissure, skin tags | Rare | Characteristic |
| Appearance of the ulcers at endoscopy | Transverse, running around the bowel; a gaping ileocaecal valve | Long ulcers along the bowel, cobblestone pattern |
| Distribution | Ileocaecal, one short continuous segment | Patchy, with skipped areas, often long segments |
| Granulomas on biopsy | Large, merging, with caseation, many per section | Small, sparse, without caseation |
| Mesenteric nodes with broken-down centres on CT | Characteristic | Uncommon |
| AFB, GeneXpert or culture | May be positive — and that settles it | Negative |
The reason this matters so much more here than in Europe or North America is a matter of consequence, not of interest. Steroids, thiopurines and biological drugs are the correct treatment for Crohn’s disease and are dangerous in undiagnosed tuberculosis: given to a patient who actually has tuberculosis, they can let the infection spread throughout the body, and that turn of events can be fatal. So the order is fixed and it is not negotiable — tuberculosis is excluded, or a full trial of ATT is completed, before anyone is immunosuppressed for presumed Crohn’s disease. Where immunosuppression genuinely cannot wait and latent tuberculosis is suspected, the latent infection is treated first.
The error also runs the other way, and it costs months: treating Crohn’s disease as tuberculosis delays the treatment that would have worked. That is precisely why the eight-week look is booked in advance rather than arranged when someone remembers. Symptoms improve in both diseases. Only the lining tells you which one you are treating.
Standard treatment for drug-sensitive intestinal tuberculosis is six months of tablets: two months of four drugs — isoniazid, rifampicin, pyrazinamide and ethambutol — followed by four months of isoniazid and rifampicin. Six months is enough; that is settled by randomised evidence, and extending the course to nine or twelve months is a specific decision made for a slow responder or for extensive disease, not a routine precaution.
What the six months involve in practice. Doses are set by weight, following the national programme. Pyridoxine goes with the isoniazid to protect the nerves. Liver function is checked before treatment and monitored during it, because drug-induced hepatitis is the commonest reason a course gets interrupted. Vision is asked about while ethambutol is being taken, and uric acid watched on pyrazinamide. Nutrition is treated as part of the treatment rather than as advice — weight at every visit, protein intake, anaemia corrected, diabetes brought under control, because a malnourished patient responds to ATT poorly. The case is notified as the national programme requires, contacts are screened, and HIV and diabetes are managed alongside. None of that is paperwork; it is the part of the treatment that decides whether the disease comes back.
Where the diagnosis was indeterminate, the same tablets double as the diagnostic test:
Two things about response are counter-intuitive and both come up constantly. Symptoms improving is not proof of tuberculosis — they improve in Crohn’s disease too, which is why healing of the lining is the endpoint. And symptoms briefly worsening soon after ATT is started is not proof of failure: it can be a paradoxical reaction as the body responds. That is a reason to reassess adherence, drug sensitivity and the diagnosis, not to abandon the tablets reflexively.
Surgery treats the complications of intestinal tuberculosis. It does not treat intestinal tuberculosis. The operation is indicated for a blockage that will not settle with conservative treatment and tablets, for a perforation, for bleeding that cannot be controlled, for a fistula or an abscess that cannot be drained, and where a mass cannot be cleared of cancer any other way. Everything about the operation is then governed by one principle: conserve bowel. Repeated or generous resections in a young patient produce short bowel syndrome, and that — not the tuberculosis — becomes the problem they live with.
What that means at the table:
Timing is as much a part of the operation as the technique. Where the surgery can wait, ATT and nutritional support are started first — two to four weeks of tablets and feeding before an elective operation is time that reduces leaks and improves recovery, and operating on an untreated, malnourished tuberculous abdomen does the opposite. The tablets continue right through the operation and the days after it, by tube or by vein if eating is interrupted. Before an elective procedure the highest-yield preparation is nutritional: albumin, anaemia correction, and feeding by mouth or tube. Where an emergency operation is needed, the site of a possible stoma is marked and discussed beforehand in every case.
The complications of bowel surgery in a tuberculous abdomen are the ordinary ones, but they occur more readily than in a well-nourished patient having the same operation for another reason: bleeding needing transfusion, wound infection, clots in the legs or lungs, a leak from the join, a stoma that may be temporary or permanent, a collection of pus inside the abdomen, bowel that is slow to start working, a leak of bowel content through the wound, a return to theatre, obstruction from adhesions years later, and a hernia at the scar. Where a long length of bowel has had to be removed, short bowel syndrome is the serious long-term consequence, and it is the reason the resection is kept limited. Dr Harsh Shah goes through every one of these personally before consent, with the figures that apply to your own nutrition, your own scans and the operation actually planned — they are not general numbers and are not quoted on a page.
And the point that has to survive the whole admission: the operation does not cure the tuberculosis. The full course of tablets is completed afterwards. Stopping them early, because the surgery went well and the patient feels better, is the commonest cause of relapse and of the drug resistance that makes the second treatment far harder than the first.
Surgery for complicated intestinal tuberculosis is covered by cashless health insurance and by CGHS and corporate schemes at Apollo Hospital, Bhat. What moves an estimate is the operation performed — a stricturoplasty is not a resection — along with whether a stoma is needed, the room category, the length of stay, and whether intensive care is required. That is why a written estimate is prepared for your own policy rather than a figure being quoted in general. The ATT tablets themselves are supplied free through the national tuberculosis programme.
Pre-authorisation is arranged by the hospital’s insurance desk before admission, and Dr Harsh Shah’s office prepares the clinical justification. For this diagnosis that justification does real work: an insurer reading “tuberculosis” may assume medical treatment only, so the reason an operation is necessary — an obstruction that has not settled, a perforation, a stricture that has turned to scar — has to be stated explicitly. Bring policy papers and identification, the approval letter, all imaging and the biopsy report, and your regular medicines in their strips. Blood-thinning and diabetes medicines need specific instructions before admission; ask for them in writing at the pre-operative visit. The ATT is not stopped for surgery — bring it with you.
★★★★★
“I am writing to express my sincere gratitude for the exceptional care provided by Dr. Harsh Shah and his team. Dr. Harsh Shah is an outstanding expert in intestinal surgery, executing complex procedures with remarkable calm and precision. Dealing with gastrointestinal diseases is incredibly stressful for both patients and their families. In my experience, what sets Dr. Harsh Shah apart is his incredible patience; he takes the time to listen to every question and provides clear, reassuring answers to every concern. As a grateful patient, I highly commend Dr. Harsh Shah and the entire team at Apollo Hospital. They did not just treat our physical condition—they truly cared for our mental and emotional well-being — Dipen Shah, Google review, Apollo Hospital, Bhat listing”
★★★★★
“I done my stoma closer operation with harsh sir such a nice and kind person never doing miss guide always give right advice polite nature. — Jigar Jadav, Google review, Gota clinic listing”
★★★★★
“From last many years I faced problem with ulcerative colitis. Thank you sir. I am completely cured of my ulcerative colitis trouble after your treatment. A way of diagnosis is brilliant. Once again thank you sir — Nisarg Shah, Google review, Gota clinic listing”
Real Google reviews from Dr Harsh Shah’s two listings, reproduced exactly as written.
In most patients, yes. A six-month course of ATT tablets cures the disease. Surgery is reserved for complications — an obstruction that will not settle, a perforation, uncontrolled bleeding, a fistula or abscess, or a mass in which cancer cannot be excluded. Being offered an operation at the first visit, before tissue has been obtained, is worth questioning.
It may well still be tuberculosis. AFB smear, GeneXpert and culture all have low yields from bowel biopsies — a positive result proves the diagnosis, a negative one does not exclude it. What matters next is the character of the granulomas, the appearance at endoscopy, the CT findings, and, if the picture stays indeterminate, a structured ATT trial with a colonoscopy at eight weeks.
Yes. In Indian practice tuberculosis is excluded, or a full ATT trial completed, before steroids, thiopurines or biological drugs are given for presumed Crohn's disease — because those drugs can allow undiagnosed tuberculosis to spread through the body. If you are on them and feeling worse rather than better, that needs review the same week.
No. Most people with intestinal tuberculosis have no active disease in the lungs, so a clear chest film is expected rather than reassuring. Equally, a positive Mantoux or IGRA does not confirm the diagnosis — past exposure is very common here. The diagnosis lives in the bowel biopsy.
Usually not. Obstruction after a completed course is most often a fibrotic stricture — burnt-out scar left behind by healed disease rather than active infection. More ATT will not open a scar. What helps is imaging to define it, and then endoscopic dilatation or a stricturoplasty.
Only a minority of patients need surgery at all, and a stoma is mainly used where the bowel has perforated or the abdomen is contaminated and malnourished — situations in which joining the bowel is more dangerous than diverting it. Where a stoma is made in these circumstances it is usually temporary, and closing it later is a far smaller operation.
Shah’s Gastro, Cancer & Robotic Surgery Centre
Gota, Ahmedabad, Gujarat
Google rating 4.89 from 216 reviews
Dr Harsh Shah consults at two addresses: the clinic at Gota, Ahmedabad, and Apollo Hospital at Bhat, Gandhinagar.
Patients travel to Dr Harsh Shah from across Gujarat and from Rajasthan and Madhya Pradesh. This disease is treated over six months rather than in a single visit, so the tablets and the monthly monitoring are arranged close to home wherever possible, with the endoscopy, the eight-week decision and any surgery here. Send the colonoscopy report and the CT on WhatsApp before travelling and the visit is planned around what they already show.
Been told you have Crohn's disease and offered steroids, without tuberculosis being ruled out first? That is the one sequence worth stopping to check, and it is checked on the biopsy, not on the scan. Call +91-63555-64601 · WhatsApp Dr Harsh Shah's office
Swasth Parivar: twice a month, practical advice on recovery, diet and warning signs. No advertising. Stop any time.
Your number is used for these updates and for the clinic to reach you. It is never sold or passed on. To stop, reply STOP on WhatsApp.
